Verastem Oncology Presents Data on Two Lead Drug Candidates at ASCO 2018 Annual Meeting

On June 4, 2018 Verastem, Inc. (NASDAQ:VSTM) (Verastem Oncology or the Company), a biopharmaceutical company focused on developing and commercializing medicines to improve the survival and quality of life of cancer patients, reported the presentation of five posters highlighting data for its two lead drug candidates, duvelisib and defactinib, at the 54th Annual Meeting of the American Society of Clinical Oncology (ASCO) (Free ASCO Whitepaper) being held June 1-5, 2018 in Chicago (Press release, Verastem, JUN 4, 2018, View Source;p=RssLanding&cat=news&id=2353079 [SID1234527157]).

Schedule your 30 min Free 1stOncology Demo!
Discover why more than 1,500 members use 1stOncology™ to excel in:

Early/Late Stage Pipeline Development - Target Scouting - Clinical Biomarkers - Indication Selection & Expansion - BD&L Contacts - Conference Reports - Combinatorial Drug Settings - Companion Diagnostics - Drug Repositioning - First-in-class Analysis - Competitive Analysis - Deals & Licensing

                  Schedule Your 30 min Free Demo!

Duvelisib is a first-in-class oral dual inhibitor of phosphoinositide 3-kinase (PI3K)-delta and PI3K-gamma that is currently being developed for the treatment of relapsed or refractory chronic lymphocytic leukemia/small lymphocytic lymphoma (CLL/SLL) and follicular lymphoma (FL). In addition, duvelisib is being studied in other hematologic malignancies including peripheral T cell lymphoma (PTCL). In April, the U.S. Food and Drug Administration (FDA) accepted with Priority Review Verastem Oncology’s New Drug Application for duvelisib, which has an FDA target action date of October 5, 2018. Defactinib is an oral small molecule inhibitor of focal adhesion kinase (FAK) and is currently being evaluated in combination with immunotherapeutic agents for the treatment of various cancers including pancreatic, ovarian and non-small cell lung cancer, and mesothelioma.

"The DUO crossover extension data reported at ASCO (Free ASCO Whitepaper) this year build upon the previously reported positive Phase 3 DUO study results and further support duvelisib’s potential as an oral treatment option for patients with relapsed or refractory CLL/SLL," said Diep Le, MD, PhD, Chief Medical Officer of Verastem Oncology. "Post-crossover, oral duvelisib monotherapy demonstrated robust clinical activity with a 73% overall response rate (ORR) and a 15-month median PFS in the 89 patients that had previously received ofatumumab on DUO and subsequently progressed . Duvelisib monotherapy also demonstrated a manageable safety profile, with results from this study consistent with the well-characterized safety profile of duvelisib monotherapy in previous studies. It is encouraging to see such a robust response to duvelisib monotherapy, similar to response observed in the parent DUO study, in patients that had failed an additional line of therapy and needed a new treatment option."

Jonathan Pachter, PhD, Chief Scientific Officer of Verastem Oncology, commented, "The presented research by Drs. Casulo and Weaver continues to provide important evidence that the dual PI3K-delta/PI3K-gamma inhibitory activity of duvelisib results in beneficial anti-tumor effects on both the cancer cells and their supportive tumor microenvironment (TME) which has the potential to enhance clinical efficacy and improve outcomes for patients battling CLL/SLL and FL."

Dr. Le added, "Dr. Andrea Wang-Gillam presented initial results from an ongoing Phase 1 study evaluating our lead FAK inhibitor defactinib in combination with pembrolizumab and gemcitabine in patients with advanced pancreatic cancer. The triplet appears to be well tolerated, the recommended Phase 2 dose has been established, and the expansion phase of the study is ongoing. In addition, promising signs of clinical activity have been observed with 3 pancreatic cancer patients treated beyond 250 days, including a confirmed partial response and the other 2 patients with stable disease. All 3 of these patients have also shown meaningful reductions (57-96%) in the pancreatic cancer marker CA19-9. Analysis of paired biopsies have also shown that this treatment induced desirable biomarker changes including increased proliferating CD8+ T cells and reduced immunosuppressive Tregs and macrophages. Treatment of pancreatic cancer represents a very important unmet need for patients, and these initial results are certainly encouraging."

Details for the ASCO (Free ASCO Whitepaper) 2018 presentations are as follows:

Duvelisib

Title: The efficacy of duvelisib monotherapy following disease progression on ofatumumab monotherapy in patients with relapsed/refractory CLL or SLL in the DUO crossover extension study
Lead author: Dr. Bryone Kuss, Flinders Medical Centre
Abstract #: 7533
Summary: In the previously reported Phase 3 DUO study oral duvelisib monotherapy achieved a statistically significant improvement in median progression-free survival (mPFS) compared to ofatumumab in patients with relapsed or refractory CLL/ SLL (13.3 months versus 9.9 months, respectively; HR=0.52; p<0.0001), along with a manageable safety profile (Flinn, ASH (Free ASH Whitepaper) 2017). The results reported here are from the open-label, DUO crossover extension study where patients with confirmed progressive disease (PD) following treatment with ofatumumab in DUO were given the option to receive treatment with duvelisib. Duvelisib 25mg BID was administered until PD, intolerance, death, or study withdrawal and responses were determined by investigators using modified IWCLL/IWG criteria.

Among the 89 evaluable patients (median three prior therapies (range 2-8), oral duvelisib monotherapy achieved a 73% overall response rate (ORR; 95% CI: 64, 82; 5% complete response with incomplete marrow recovery (CRis), 68% partial responses [PRs]) in the extension study. While on ofatumamab in the DUO study, these 89 patients had a 28% ORR (95% CI: 19, 37; 1% complete response (CR), 27% PRs). The mPFS for duvelisib in the extension study was 15 months (95% CI: 10, 17). While on ofatumamab in the DUO study, these 89 patients had a mPFS of 9 months (95% CI: 9, 11), per investigator’s assessment. Notably, 83% of patients in the duvelisib arm post-crossover had >50% reductions in the size of their target nodal lesions. These same 89 patients had 27% reductions in the size of their target nodal lesions in the DUO ofatumumab arm. Median exposure to duvelisib in the extension study was 32 weeks. The safety profile of duvelisib monotherapy was manageable and consistent with what was observed in the Phase 3 DUO study. The most common Grade ≥3 treatment-emergent adverse events were neutropenia (22%), diarrhea (17%), colitis (9%), pneumonia (9%), rash (5%) and pyrexia (4%). These data build upon the previously reported positive DUO results and further support oral duvelisib monotherapy as an effective oral treatment option for patients with relapsed or refractory CLL/SLL.

A copy of the poster presentation will be available here.

Title: The effect of duvelisib, a dual inhibitor of PI3K-δ,γ, on components of the tumor microenvironment in previously untreated follicular lymphoma
Lead author: Dr. Carla Casulo, University of Rochester, Wilmot Cancer Center
Abstract #: 7579
Summary: In previously reported data from the CONTEMPO trial, treatment-naive FL patients treated with duvelisib in combination with rituxumab had an ORR of 93% (36% CRR), and an ORR of 89% (41% CRR) was observed for patients treated with duvelisib in combination with obinutuzumab. In this study, blood samples from healthy volunteers and FL patients treated in the CONTEMPO study, both pre- and post-duvelisib treatment, were analyzed. Ex vivo and in vitro PI3K-γ assays and PI3K-δ assays, with PI3K-δ-selective (idelalisib, TGR-1202, IPI-3063) and PI3K-γ-selective (IPI-549) inhibitors were compared.

Duvelisib and idelalisib potently inhibited LPS-induced human monocytes via PI3K-δ, compared with the PI3K-γ selective IPI-549. For TGR-1202, the IC50 was below the recommended Phase 2 dose (RP2D) clinical exposure. Duvelisib and IPI-549 potently inhibited PI3K-γ dependent fMLP-stimulated human monocytes compared to idelalisib and TGR-1202. In FL patients treated with duvelisib, these PI3K-γ and PI3K-δ selective assays were inhibited 1-4 hours post treatment. Consistent with a PI3K-γ mechanism, both duvelisib and IPI-549 inhibited macrophage polarization to M2, reduced CXCL12-induced macrophage migration, and blocked CXCL12-induced T cell migration, which was not observed with PI3K-δ inhibitor IPI-3063. Collectively, these results support the thesis that duvelisib disrupts PI3K- δ,γ function in FL patients inhibiting the TME through cancer-supportive macrophages and T cells.

A copy of the poster presentation will be available here.

Title: The PRIMO study: A phase 2 study of duvelisib efficacy and safety in patients with relapsed or refractory peripheral t-cell lymphoma (PTCL)
Lead author: Dr. Steven Horwitz, Memorial Sloan Kettering Cancer Center
Abstract #: TPS7590
Summary: This poster describes the PRIMO study, a Phase 2 open-label clinical trial evaluating duvelisib monotherapy in adult patients with PTCL, one of the most aggressive forms of non-Hodgkin lymphoma (NHL). The study employs a dose optimization phase (DOP) and an Expansion Phase (EP). The primary objectives are to identify the optimal dose of duvelisib in PTCL and examine the efficacy, safety, and tolerability of duvelisib at the optimal dose. The study is expected to enroll up to 120 patients with histologically confirmed PTCL subtypes of PTCL-NOS, angioimmunoblastic TCL, anaplastic large cell lymphoma, and natural-killer TCL. Disease responses will be measured by PET-CT scanning as assessed by an independent review committee per IWG criteria. The primary endpoint is ORR (CR + PR) in all patients receiving the optimal dose for at least 1 cycle in either phase. Secondary endpoints include safety, duration of response, and PFS. This study is open for enrollment. Duvelisib has been granted Fast Track designation by the U.S. Food and Drug Administration (FDA) for the treatment of patients with PTCL who have received at least one prior therapy.

A copy of the poster presentation will be available here.

Title: Duvelisib inhibition of chemokines in patients with CLL (DUO study) and iNHL (DYNAMO study)
Lead author: Dr. David Weaver, Verastem Oncology
Abstract #: 12048
Summary: PI3K-δ inhibition directly targets proliferation and survival of malignant leukemia and lymphoma cells, while PI3K-γ inhibition modulates the TME through key support cells, including tumor-associated macrophages, nurse-like stroma and T cells, and via soluble factors stimulating tumor growth, survival and migration. Serum samples from patients in the Phase 3 DUO study in relapsed/refractory CLL/SLL and the Phase 2 DYNAMO study in relapsed/refractory indolent NHL were collected at baseline and at C2D1 and used for correlative studies of 24 chemokines, cytokines and serum factors.

In serum samples from the DUO study, CCL1, CCL17, CXCL9, CXCL10, CXCL11, and IL-10 were reduced in patients treated with duvelisib (median 43.8%) but not in those treated with ofatumumab (p≤0.0009). Eight chemokines were reduced in both treatment arms, but the level of reduction was significantly greater for duvelisib-treated patients (median 64.6% for duvelisib versus 26.8% for ofatumumab [p≤0.001]). Many of the chemokines inhibited following duvelisib treatment are associated with the TME, including TNFα, IL-10, IL2Rα, IL12P40, CCL1, CCL17, CCL19, CXCL9, CXCL10, CXCL11, and CXCL13. In serum samples from the DYNAMO study, 13 corresponding chemokines were also inhibited (p≤0.008), including TME factors. Reductions occurred rapidly (by C2D1) in both studies. In DUO, there was a correlation between duration of response and reduction of the following chemokines: CCL17, CXCL11, IL-6, TRAIL, VEGF-D and TPO. These data support the hypothesis that treatment with duvelisib results in significant reduction of chemokines potentially derived from the tumor cells and TME and that further investigation of the effects of duvelisib on TME pharmacodynamic markers is warranted.

A copy of the poster presentation will be available here.

Defactinib

Title: Phase I study of defactinib combined with pembrolizumab and gemcitabine in patients with advanced cancer
Lead author: Dr. Andrea Wang-Gillam, Washington University in St. Louis
Abstract #: 2561
Summary: FAK is consistently hyperactivated in multiple tumor types including pancreatic ductal adenocarcinoma (PDAC). Previously reported preclinical research showed that FAK and PD-1 inhibitors elicit significant tumor regression, and a maximal response is achieved by combining FAK and PD-1 inhibitors with gemcitabine, suggesting the need for a cytotoxic agent to bolster antigen presentation. In this ongoing Phase 1, dose-escalation study, defactinib is being evaluated in combination with Merck’s PD-1 inhibitor pembrolizumab and gemcitabine in patients with PDAC.

The dose escalation cohort has been completed with a total of 20 patients with refractory solid tumors. Of the 15 patients evaluable for treatment response, 1 (7%) achieved a confirmed PR and 8 (53%) achieved stable disease (SD). Of the 8 PDAC patients, 1 (13%) achieved a confirmed PR and 3 (38%) achieved SD. The median time on treatment was 132 days for all evaluable patients and 158 days for patients with PDAC. Paired biopsies from PDAC patients showed increased proliferating CD8+ T cells and decreased T regs in patients with controlled disease compared to patients with progressive disease. The combination regimen was well tolerated with no dose limiting toxicities, and therefore the RP2D dose was established as defactinib (400mg BID, Days 1-21), pembrolizumab (200mg, Day 1) and gemcitabine (1,000mg/m2, Day 1 and 8). The common treatment-emergent adverse events were anorexia (50%), fatigue (40%), diarrhea (40%), fever (40%) and vomiting (35%), but nearly all were Grade 1/2. There was 1 case of Grade ≥3 diarrhea. An expansion cohort in patients with PDAC is currently ongoing.

A copy of the poster presentation will be available here.

About Duvelisib

Duvelisib is a first-in-class investigational oral, dual inhibitor of phosphoinositide 3-kinase (PI3K)-delta and PI3K-gamma, two enzymes known to help support the growth and survival of malignant B-cells and T-cells. PI3K signaling may lead to the proliferation of malignant B- and T-cells and is thought to play a role in the formation and maintenance of the supportive tumor microenvironment.1,2,3 Duvelisib was evaluated in late- and mid-stage extension trials, including DUO, a randomized, Phase 3 monotherapy study in patients with relapsed or refractory chronic lymphocytic leukemia/small lymphocytic lymphoma (CLL/SLL),4 and DYNAMO, a single-arm, Phase 2 monotherapy study in patients with refractory indolent non-Hodgkin lymphoma (iNHL).5 Both DUO and DYNAMO achieved their primary endpoints. Verastem Oncology’s New Drug Application (NDA) requesting the full approval of duvelisib for the treatment of patients with relapsed or refractory CLL/SLL, and accelerated approval for the treatment of patients with relapsed or refractory follicular lymphoma (FL) was accepted for filing by the U.S. Food and Drug Administration (FDA), granted Priority Review and assigned a target action date of October 5, 2018. Duvelisib is also being developed by Verastem Oncology for the treatment of peripheral T-cell lymphoma (PTCL), and is being investigated in combination with other agents through investigator-sponsored studies.6 Information about duvelisib clinical trials can be found on www.clinicaltrials.gov.

About Defactinib

Defactinib is an investigational inhibitor of focal adhesion kinase (FAK), a non-receptor tyrosine kinase that mediates oncogenic signaling in response to cellular adhesion and growth factors.7 Based on the multi-faceted roles of FAK, defactinib is used to treat cancer through modulation of the tumor microenvironment and enhancement of anti-tumor immunity.8,9 Defactinib is currently being evaluated in three separate clinical collaborations in combination with immunotherapeutic agents for the treatment of several different cancer types including pancreatic cancer, ovarian cancer, non-small cell lung cancer (NSCLC), and mesothelioma. These studies are combination clinical trials with pembrolizumab and avelumab from Merck & Co. and Pfizer/Merck KGaA, respectively.10,11,12 Information about these and additional clinical trials evaluating the safety and efficacy of defactinib can be found on www.clinicaltrials.gov.

Insights from ASCO 2018

1stOncology’s ‘Commercial Interests at ASCO (Free ASCO Whitepaper) 2018‘ report highlights the landscape of commercial oncology drug development presenting abstracts at the 2018 ASCO (Free ASCO Whitepaper) meeting. Below is some interesting headline points our analyst team picked from ASCO (Free ASCO Whitepaper) 2018, but if you would like to get the full picture, we invite you to 48 hours of free access to our ASCO (Free ASCO Whitepaper) 2018 whitepaper. Sign up here for your free access.

(P.S. Did you know that 1stOncology Conference™ service covers the 10 major meetings in oncology? Joining 1stOncology Conference™ secures your knowledge of what is driving the AACR, ASCO (Free ASCO Whitepaper), ASGCT (Free ASGCT Whitepaper), ASH (Free ASH Whitepaper), EORTC-NCI-AACR (Free EORTC-NCI-AACR Whitepaper), ESMO (Free ESMO Whitepaper), SITC (Free SITC Whitepaper) and BIO (International, Europe and Asia) meetings for a small additional cost to your conference expenses. Your membership is backed by our completely risk free 30-day full refund guarantee, so get started here today!)

Two out of Five Drugs at ASCO (Free ASCO Whitepaper) 2018 are in Immuno-Oncology:

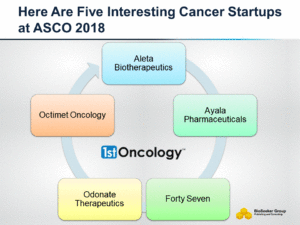
Five Interesting Startups Presenting Abstracts at ASCO (Free ASCO Whitepaper) 2018:

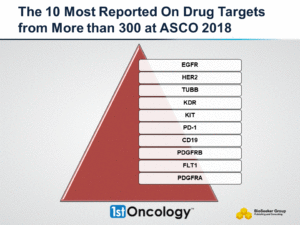
The 10 Most Reported-On Drug Targets from More than 300 at ASCO (Free ASCO Whitepaper) 2018:

There are close to 30 First-in-Class Drug Targets at ASCO (Free ASCO Whitepaper) 2018:


Sign up here for your free 48 access to our ASCO (Free ASCO Whitepaper) 2018 Whitepaper

or

Join our 1stOncology Conference™ service, completely risk free 30-day full refund guarantee!


Schedule your 30 min Free 1stOncology Demo!
Discover why more than 1,500 members use 1stOncology™ to excel in:

Early/Late Stage Pipeline Development - Target Scouting - Clinical Biomarkers - Indication Selection & Expansion - BD&L Contacts - Conference Reports - Combinatorial Drug Settings - Companion Diagnostics - Drug Repositioning - First-in-class Analysis - Competitive Analysis - Deals & Licensing

                  Schedule Your 30 min Free Demo!


Exelixis Announces Results from Sub-Group Analyses of the Phase 3 Pivotal CELESTIAL Trial of Cabozantinib for Advanced Hepatocellular Carcinoma Presented at ASCO 2018

On June 3, 2018 Exelixis, Inc. (Nasdaq: EXEL) reported results from sub-group analyses of the CELESTIAL phase 3 pivotal trial of cabozantinib in advanced hepatocellular carcinoma (HCC) comparing outcomes by duration of sorafenib treatment in patients whose only prior treatment was sorafenib and outcomes based on age (Press release, Exelixis, JUN 3, 2018, View Source;p=RssLanding&cat=news&id=2352879 [SID1234527074]). The findings, presented in two posters at the American Society of Clinical Oncology (ASCO) (Free ASCO Whitepaper) 2018 Annual Meeting during the Gastrointestinal (Noncolorectal) Cancer Poster Session from 8:00 – 11:00 a.m. CDT in Hall A, showed that cabozantinib improved overall survival (OS) and progression-free survival (PFS) compared with placebo irrespective of duration of prior sorafenib treatment or age category.

Schedule your 30 min Free 1stOncology Demo!
Discover why more than 1,500 members use 1stOncology™ to excel in:

Early/Late Stage Pipeline Development - Target Scouting - Clinical Biomarkers - Indication Selection & Expansion - BD&L Contacts - Conference Reports - Combinatorial Drug Settings - Companion Diagnostics - Drug Repositioning - First-in-class Analysis - Competitive Analysis - Deals & Licensing

                  Schedule Your 30 min Free Demo!

"We’re pleased with the encouraging CELESTIAL subgroup data presented at ASCO (Free ASCO Whitepaper), which showed that cabozantinib provided benefits to patients regardless of duration of prior sorafenib treatment or age," said Gisela Schwab, M.D., President, Product Development and Medical Affairs and Chief Medical Officer, Exelixis. "We continue to work closely with the U.S. FDA as they review the filing application for cabozantinib for previously treated advanced hepatocellular carcinoma and hope it may soon provide a new option for patients with this difficult-to-treat cancer who have few alternatives."

Outcomes in Patients who had Received Sorafenib [abstract 4088]

The sub-analysis of patients in CELESTIAL who received sorafenib as their only prior systemic therapy was presented by Robin Kate Kelley, M.D., University of California San Francisco. In this subgroup-analysis, patients were grouped by the length of time they had been treated with sorafenib (less than three months; three to six months; more than six months) to assess the effect of cabozantinib in patients with varying benefit from prior sorafenib. In all three groups, cabozantinib improved OS and PFS versus placebo:

Treatment-related grade 3 or 4 adverse events (AEs) that occurred in at least 5 percent of any patient group were palmar-plantar erythrodysesthesia, aspartate aminotransferase increased, hypertension, fatigue, decreased appetite, diarrhea, asthenia and anemia.

Outcomes in Patients Based on Age [abstract 4090]

The sub-analysis evaluating patients in the CELESTIAL trial based on age was presented by Lorenza Rimassa, M.D., Humanitas Clinical and Research Center. In this sub-analysis, patients were grouped as younger than 65 years of age and 65 years of age and older. The findings showed OS and PFS were consistently improved with cabozantinib versus placebo in each age category:

Treatment-related grade 3 or 4 AEs occurred in at least 5 percent of either age group and were similar in nature and frequency to the AEs that occurred in patients who received sorafenib as their only prior systemic therapy.

An encore of the CELESTIAL trial data originally presented at the 2018 American Society of Clinical Oncology (ASCO) (Free ASCO Whitepaper) Gastrointestinal Cancers Symposium (ASCO-GI) will be presented by Dr. Ghassan K. Abou-Alfa, Memorial Sloan Kettering Cancer Center, during the Gastrointestinal (Noncolorectal) Cancer Poster Discussion Session today from 4:45 – 6:00 p.m. CDT in Hall D2 [abstract 4019].

The CELESTIAL trial was the basis for Exelixis’ supplemental New Drug Application filed with the U.S. Food and Drug Administration (FDA) for CABOMETYX (cabozantinib) tablets as a treatment for patients with previously treated advanced HCC. The Prescription Drug User Fee Act action date for this application is January 14, 2019. On March 28, 2018, our partner Ipsen announced that they received validation of the application for variation to the CABOMETYX marketing authorization from the European Medicines Agency, the European regulatory authority, for the addition of a new indication for patients with previously treated advanced HCC.

About the CELESTIAL Study

CELESTIAL is a phase 3 randomized, double-blind, placebo-controlled study of cabozantinib in patients with advanced HCC conducted at more than 100 sites globally in 19 countries. The trial was designed to enroll 760 patients with advanced HCC who received prior sorafenib and may have received up to two prior systemic cancer therapies for HCC and had adequate liver function. Enrollment of the trial was completed in September 2017. Patients were randomized 2:1 to receive 60 mg of cabozantinib once daily or placebo and were stratified based on etiology of the disease (hepatitis C, hepatitis B or other), geographic region (Asia versus other regions) and presence of extrahepatic spread and/or macrovascular invasion (yes or no). No cross-over was allowed between the study arms during the blinded treatment phase of the trial. The primary endpoint for the trial is overall survival, and secondary endpoints include objective response rate and progression-free survival. Exploratory endpoints include patient-reported outcomes, biomarkers and safety.

Results of the trial were first presented by Dr. Abou-Alfa at 2018 American Society of Clinical Oncology (ASCO) (Free ASCO Whitepaper) Gastrointestinal Cancers Symposium in January 2018.

About HCC

Liver cancer is the second-leading cause of cancer death worldwide, accounting for more than 700,000 deaths and nearly 800,000 new cases each year.1 In the U.S., the incidence of liver cancer has more than tripled since 1980.2 HCC is the most common form of liver cancer, making up about three-fourths of the estimated nearly 42,000 new cases in the U.S. in 2018. HCC is the fastest-rising cause of cancer-related death in U.S.3 Without treatment, patients with advanced HCC usually survive less than 6 months.4

About CABOMETYX (cabozantinib)

CABOMETYX tablets are approved in the United States for the treatment of patients with advanced RCC. CABOMETYX tablets are also approved in the European Union, Norway, Iceland, Australia, Switzerland and South Korea for the treatment of advanced RCC in adults who have received prior VEGF-targeted therapy, and in the European Union for previously untreated intermediate- or poor-risk advanced RCC. In 2016, Exelixis granted Ipsen exclusive rights for the commercialization and further clinical development of cabozantinib outside of the United States and Japan. In 2017, Exelixis granted exclusive rights to Takeda Pharmaceutical Company Limited for the commercialization and further clinical development of cabozantinib for all future indications in Japan, including RCC and HCC.

Please see Important Safety Information below and full U.S. prescribing information at View Source

U.S. Important Safety Information

Hemorrhage: Severe and fatal hemorrhages have occurred with CABOMETYX. In two RCC studies, the incidence of Grade ≥ 3 hemorrhagic events was 3% in CABOMETYX-treated patients. Do not administer CABOMETYX to patients that have or are at risk for severe hemorrhage.
Gastrointestinal (GI) Perforations and Fistulas: In RCC studies, fistulas were reported in 1% of CABOMETYX-treated patients. Fatal perforations occurred in patients treated with CABOMETYX. In RCC studies, gastrointestinal (GI) perforations were reported in 1% of CABOMETYX-treated patients. Monitor patients for symptoms of fistulas and perforations, including abscess and sepsis. Discontinue CABOMETYX in patients who experience a fistula which cannot be appropriately managed or a GI perforation.
Thrombotic Events: CABOMETYX treatment results in an increased incidence of thrombotic events. In RCC studies, venous thromboembolism occurred in 9% (including 5% pulmonary embolism) and arterial thromboembolism occurred in 1% of CABOMETYX-treated patients. Fatal thrombotic events occurred in the cabozantinib clinical program. Discontinue CABOMETYX in patients who develop an acute myocardial infarction or any other arterial thromboembolic complication.
Hypertension and Hypertensive Crisis: CABOMETYX treatment results in an increased incidence of treatment-emergent hypertension, including hypertensive crisis. In RCC studies, hypertension was reported in 44% (18% Grade ≥ 3) of CABOMETYX-treated patients. Monitor blood pressure prior to initiation and regularly during CABOMETYX treatment. Withhold CABOMETYX for hypertension that is not adequately controlled with medical management; when controlled, resume CABOMETYX at a reduced dose. Discontinue CABOMETYX for severe hypertension that cannot be controlled with anti-hypertensive therapy. Discontinue CABOMETYX if there is evidence of hypertensive crisis or severe hypertension despite optimal medical management.
Diarrhea: In RCC studies, diarrhea occurred in 74% of patients treated with CABOMETYX. Grade 3 diarrhea occurred in 11% of patients treated with CABOMETYX. Withhold CABOMETYX in patients who develop intolerable Grade 2 diarrhea or Grade 3-4 diarrhea that cannot be managed with standard antidiarrheal treatments until improvement to Grade 1; resume CABOMETYX at a reduced dose.
Palmar-Plantar Erythrodysesthesia (PPE): In RCC studies, palmar-plantar erythrodysesthesia (PPE) occurred in 42% of patients treated with CABOMETYX. Grade 3 PPE occurred in 8% of patients treated with CABOMETYX. Withhold CABOMETYX in patients who develop intolerable Grade 2 PPE or Grade 3 PPE until improvement to Grade 1; resume CABOMETYX at a reduced dose.
Reversible Posterior Leukoencephalopathy Syndrome (RPLS), a syndrome of subcortical vasogenic edema diagnosed by characteristic finding on MRI, occurred in the cabozantinib clinical program. Perform an evaluation for RPLS in any patient presenting with seizures, headache, visual disturbances, confusion or altered mental function. Discontinue CABOMETYX in patients who develop RPLS.
Embryo-fetal Toxicity may be associated with CABOMETYX. Advise pregnant women of the potential risk to a fetus. Advise females of reproductive potential to use effective contraception during CABOMETYX treatment and for 4 months after the last dose.
Adverse Reactions: The most commonly reported (≥25%) adverse reactions are: diarrhea, fatigue, nausea, decreased appetite, hypertension, PPE, weight decreased, vomiting, dysgeusia, and stomatitis.
Strong CYP3A4 Inhibitors: If concomitant use with strong CYP3A4 inhibitors cannot be avoided, reduce the CABOMETYX dosage.
Strong CYP3A4 Inducers: If concomitant use with strong CYP3A4 inducers cannot be avoided, increase the CABOMETYX dosage.
Lactation: Advise women not to breastfeed while taking CABOMETYX and for 4 months after the final dose.
Hepatic Impairment: In patients with mild to moderate hepatic impairment, reduce the CABOMETYX dosage. CABOMETYX is not recommended for use in patients with severe hepatic impairment.

Erdafitinib Phase 2 Study Results Show Promise in the Treatment of Metastatic Urothelial Cancer

On June 3, 2018 The Janssen Pharmaceutical Companies of Johnson & Johnson reported findings today from a Phase 2 study that showed treatment with erdafitinib resulted in durable responses in patients with metastatic or surgically unresectable urothelial cancer (mUC) and fibroblast growth factor receptor alterations (FGFRalt) (Press release, Johnson & Johnson, JUN 3, 2018, View Source [SID1234527110]). This is a patient population with high unmet need based on poor outcomes when treated with available therapies. Erdafitinib is a once-daily pan-FGFR inhibitor.1 FGFRs are cell proteins that, if altered, can contribute to the development of cancer.1 Alterations occur in approximately 20 percent of mUC patients.1 The results were presented at the American Society of Clinical Oncology (ASCO) (Free ASCO Whitepaper) 2018 Annual Meeting in Chicago (Abstract #4503) and have been selected for the Best of ASCO (Free ASCO Whitepaper) Meetings.1

Schedule your 30 min Free 1stOncology Demo!
Discover why more than 1,500 members use 1stOncology™ to excel in:

Early/Late Stage Pipeline Development - Target Scouting - Clinical Biomarkers - Indication Selection & Expansion - BD&L Contacts - Conference Reports - Combinatorial Drug Settings - Companion Diagnostics - Drug Repositioning - First-in-class Analysis - Competitive Analysis - Deals & Licensing

                  Schedule Your 30 min Free Demo!

"These study results are very promising, particularly as this is an area of high unmet need with patients who otherwise have very limited treatment options remaining. We hope that the response rates shown by erdafitinib could eventually give patients with metastatic or surgically unresectable urothelial cancer a new treatment option"

Tweet this
"I am very encouraged by these Phase 2 data showing that erdafitinib had promising response rates and progression-free survival in a patient population with such high unmet need," said Dr. Yohann Loriot, Senior Consultant, Department of Cancer Medicine & INSERM, Institut Gustave Roussy, University of Paris Sud, Villejuif, France. "Currently there are no targeted therapies approved for specific subsets of patients with urothelial cancer who have genetic alterations. While immune checkpoint inhibitors have led to improvements in outcomes for these patients, we are still finding that many patients do not respond to treatment."

BLC2001 (NCT02365597) is a multicentre, open-label Phase 2 study evaluating the efficacy and safety of erdafitinib in the treatment of adult patients with locally advanced or metastatic urothelial cancer, whose tumours have certain FGFR alterations.1 Ninety-nine patients were treated with an optimised dosing schedule using pharmacodynamically guided dose up-titration: a starting dose of erdafitinib at 8 mg daily, with the possibility to increase the dose to 9 mg daily based on serum phosphate levels.2 Twelve percent of patients were chemo-naïve, 89 percent of patients had received one or more lines of therapy, 43 percent of patients had received two or more prior lines of therapy, and 78 percent of patients had visceral metastases.2 There was a 40 percent confirmed overall response rate1 (RECIST 1.1;* 3% Complete Response, 37% Partial Response), a median progression-free survival of 5.5 months and median overall survival of 13.8 months.2 In patients who experienced grade 3 adverse events (AEs), the most common were, stomatitis (9%) and diarrhoea (4%).1 Seven patients discontinued due to treatment-related AEs.2

"These study results are very promising, particularly as this is an area of high unmet need with patients who otherwise have very limited treatment options remaining. We hope that the response rates shown by erdafitinib could eventually give patients with metastatic or surgically unresectable urothelial cancer a new treatment option," said Dr Ivo Winiger-Candolfi, Europe, Middle East and Africa (EMEA) Oncology Therapeutic Area Lead, Janssen. "The successful development of new oncology therapies, such as erdafitinib, is an example of our precision medicine approach: providing the right patient, with the right treatment, at the right time. We recognise that every patient is unique and that by accounting for individual differences in people’s genes, environments and lifestyles, we can optimise the therapeutic benefit for particular groups of patients. We look forward to understanding the potential efficacy and broader safety profile of erdafitinib in both Phase 3 development as well as in combination with anti-PD1 therapy."

*RECIST (version 1.1) refers to Response Evaluation Criteria in Solid Tumors which is a standard way to measure how well a cancer patient responds to treatment and is based on whether tumours shrink, stay the same, or get bigger.3

About Urothelial Cancer

Europe has among the highest incidence rates of bladder cancer in the world and mortality rates for men are by far the highest recorded worldwide.4 It is the fifth most frequently diagnosed cancer in the EU, with about 124,000 new cases each year for both sexes.5 The majority (90%) of bladder cancer consists of urothelial carcinoma in Western Europe.6 Urothelial bladder cancer starts in the bladder lining (urothelial cells or transitional cells) and can be non-invasive or invasive.7 For patients with metastatic disease, outcomes can be poor due to the often rapid progression of the tumour and the lack of efficacious treatments.8 The relative five-year survival rate for patients with metastatic disease is five percent.9

About erdafitinib

Erdafitinib is a once-daily oral pan-fibroblast growth factor receptor (FGFR) tyrosine kinase inhibitor being evaluated by Janssen Research & Development in Phase 2 and 3 clinical trials in patients with advanced urothelial cancer.10 FGFRs are a family of receptor tyrosine kinases which may be upregulated in various tumour cell types and may be involved in tumour cell proliferation, tumour angiogenesis and tumour cell survival.11 In 2008, Janssen entered into an exclusive worldwide license and collaboration agreement with Astex Therapeutics Ltd. to develop and commercialise erdafitinib.

Erdafitinib received Breakthrough Therapy Designation from the U.S. Food and Drug Administration in March 2018.12 The aim is to move towards regulatory submission with the Phase 2 data and continue to pursue erdafitinib in Phase 3 clinical development, as well as in combination with anti-PD-1 therapy.

Astellas and Seattle Genetics Present at ASCO 2018 on Enfortumab Vedotin in Patients with Locally Advanced or Metastatic Urothelial Cancer Previously Treated with Checkpoint Inhibitor Therapy

On June 3, 2018 Astellas Pharma Inc. (TSE: 4503, President and CEO: Kenji Yasukawa, Ph.D., "Astellas") and Seattle Genetics, Inc. (Nasdaq: SGEN) reported the presentation of updated phase 1 data of enfortumab vedotin, an investigational antibody-drug conjugate (ADC), at the American Society of Clinical Oncology (ASCO) (Free ASCO Whitepaper) 2018 Annual Meeting in Chicago (Press release, Astellas, JUN 3, 2018, View Source [SID1234527059]). In this phase 1 study (EV-101), enfortumab vedotin was evaluated as monotherapy for patients with metastatic urothelial cancer including patients who previously received a checkpoint inhibitor.i This phase 1 study is part of a broader program focused on investigating enfortumab vedotin in both monotherapy and in combination with a checkpoint inhibitor for locally advanced or metastatic urothelial cancer.

Schedule your 30 min Free 1stOncology Demo!
Discover why more than 1,500 members use 1stOncology™ to excel in:

Early/Late Stage Pipeline Development - Target Scouting - Clinical Biomarkers - Indication Selection & Expansion - BD&L Contacts - Conference Reports - Combinatorial Drug Settings - Companion Diagnostics - Drug Repositioning - First-in-class Analysis - Competitive Analysis - Deals & Licensing

                  Schedule Your 30 min Free Demo!

(PRNewsfoto/Astellas Pharma Inc.)

"Many patients with locally advanced or metastatic urothelial cancer previously treated with checkpoint inhibitors have a poor prognosis and limited subsequent treatment options," said Jonathan E. Rosenberg, M.D., medical oncologist at Memorial Sloan Kettering Cancer Center and presenter of the updated phase 1 data at ASCO (Free ASCO Whitepaper). "Data from the ongoing study support the potential of enfortumab vedotin in locally advanced or metastatic urothelial cancer, based on the objective response rate and preliminary estimates of survival."

"We are encouraged by these updated data for enfortumab vedotin, which further support the rapid expansion of a comprehensive clinical trial program and the registrational study that is already underway in metastatic urothelial cancer," said Steven Benner, M.D., Senior Vice President and Global Therapeutic Area Head, Oncology Development, Astellas. "We look forward to working closely with our partner, Seattle Genetics, as we continue to evaluate enfortumab vedotin for patients with metastatic urothelial cancer."

Robert Lechleider, M.D., Senior Vice President, Clinical Development at Seattle Genetics added, "These ASCO (Free ASCO Whitepaper) data from the phase 1 study of enfortumab vedotin further support its Breakthrough Therapy Designation from the FDA, and the rationale for our ongoing pivotal trial, EV-201. We look forward to completing enrollment of the EV-201 pivotal trial for patients with metastatic urothelial cancer who have received both a platinum-based therapy and a checkpoint inhibitor. Positive data in this patient subgroup may represent a potential expedited registration pathway."

The following updated results were presented by Dr. Rosenberg:

Updated Results from the Enfortumab Vedotin Phase 1 (EV-101) Study in Patients with Metastatic Urothelial Cancer: (Abstract #4504, oral abstract session on Sunday, June 3 from 9:12-9:24 a.m. CT)1

Study Design

A total of 112 patients with metastatic urothelial cancer treated with 1 or more prior chemotherapy or who were ineligible for cisplatin received a 30-minute infusion of enfortumab vedotin at 1.25 mg/kg on day 1, 8 and 15 of each 28-day cycle.ii
Sixty-three percent of patients had received 2 or more prior therapies in the metastatic setting.1
The primary objective of the study was tolerability. A secondary objective was antitumor activity, which was assessed by investigators every 8 weeks.2
Study Results

Of 112 evaluable patients, confirmed complete responses were observed in 4 patients and confirmed partial responses were observed in 41 patients, with an overall response rate of 41 percent.1
The most commonly reported treatment-related adverse event was All Grade fatigue (54 percent). Anemia (8 percent), hyponatremia (7 percent), urinary tract infection (7 percent) and hyperglycemia (6 percent) were the most common ≥ Grade 3 AEs.1 Four patients experienced a fatal treatment-related adverse event (respiratory failure, urinary tract obstruction, diabetic ketoacidosis, multi-organ failure).2
Additionally, the ORR in the 89 patients with prior checkpoint inhibitor therapy was 40 percent, 44 percent in the 23 patients who had not been treated with a checkpoint inhibitor, and 39 percent in the 33 patients with liver metastases.1
For all enrolled patients, the interim median overall survival was 13.6 months, the overall median duration of response was 5.75 months and the median progression-free survival was 5.4 months.1
EV-201 Study: A Single-Arm, Open-Label, Multicenter Study of Enfortumab Vedotin for Treatment of Patients with Locally Advanced or Metastatic Urothelial Cancer Who Previously Received Immune Checkpoint Inhibitor Therapy (Abstract #TPS4590, poster session on Saturday, June 2 from 8:00-11:30 a.m. CT)iii

In addition, the EV-201 trial in progress poster was presented at the meeting. EV-201 is an ongoing single-arm, single-agent pivotal phase 2 clinical trial of enfortumab vedotin for patients with locally advanced or metastatic urothelial cancer who have been previously treated with checkpoint inhibitor therapy, including those who had also been treated with a platinum chemotherapy and those who were platinum naive.3

More information about the enfortumab vedotin clinical trials can be found at View Source

About Urothelial Cancer
According to the American Cancer Society, urothelial cancer, also known as transitional cell carcinoma (TCC), is the most common type of bladder canceriv (90 percent of casesv). Approximately 81,000 people in the U.S. are anticipated to be diagnosed with bladder cancer during 2018.vi Bladder cancer is the fourth most common cancer in men, but is less common in women.6 Outcomes are poor for people diagnosed with metastatic disease, with a five-year survival rate of 4.8 percent.vii

About Enfortumab Vedotin
Enfortumab vedotin is an investigational ADC composed of an anti-Nectin-4 monoclonal antibody attached to a microtubule-disrupting agent, MMAE, using Seattle Genetics’ proprietary, linker technology. Enfortumab vedotin targets Nectin-4, a cell adhesion molecule identified as an ADC target by Astellas, which is expressed on many solid tumors.